
What people are usually offered
- Rest until the pain settles
- A brace that limits the painful motion
- An injection or medication that masks the symptom
- A scan treated as the whole diagnosis
- Stop the work, the game, or the instrument
Clinical experience and the evidence
We combine our clinical experience with the evidence that exists for this work. The clinical results speak for themselves. Read the testimonials.
The protocols started with esports athletes who train for long sessions at low load and high repetition. We use the same approach for computer use, music, art, and other high-volume hand work.
Educational information, not a diagnosis or a promise of a specific outcome.
Peer-reviewed sources
Every major claim links to the paper behind it.
Study limits shown
Population and transfer limits are stated, not hidden.
Results in practice
Clinical experience and the available evidence, tested with real clients. Read the testimonials.
Why the usual plan stalls
Rest, a brace, an injection, or a scan can turn the volume down. Advice to stop the work, the game, or the instrument can do the same. None of those finish the job when the wrist, hand, and forearm still cannot tolerate the day you need them to tolerate.
The short version
These protocols started in clinical work with esports athletes who practice for long sessions at low external load and high repetition. We use the same framework for computer work, instrumental practice, drawing, and other manual endurance tasks because the demand pattern is related. That extension is clinical reasoning. It is not one trial that followed every group through the same protocol.
Our published work in this area includes a viewpoint on musculoskeletal injuries in esports and the physical therapist's role,[1] and the corrective-exercise and physical-training chapters in Conditioning for Esports.[2] A study from our group also measured how arm position changes the subacromial space in upper string musicians.[3] Those publications describe the population and the problem. They do not prove a specific wrist-endurance dose.
Health research has not produced good trials of these high-volume, low-load hand conditions. Reviews of tendinopathy in gaming and of esports health describe an early evidence base and call for more direct study.[4][5] Care copied from other joints and other sports is a poor fit, and that gap is one reason the traditional plan so often stops at rest, a brace, or an image.
Where research does exist, it supports a whole-person sequence: measure the person in front of us, match load to current capacity, rebuild general and task-specific tolerance, and address the nervous-system and behavioral factors that can keep someone limited. The sections below show each finding, how 1HP uses it, and where that finding stops.
The plan has four parts, and they work together.
Start with symptoms, function, red flags, and reproducible capacity, not an image in isolation.
Use enough load to create adaptation without repeatedly exceeding today’s tolerance.
Pair general exercise with a progressive return to typing, gaming, creating, music, or work.
Combine physical loading with pain education, confidence, pacing, and motor-control strategies.
Tendon biology
Pathology model + imaging study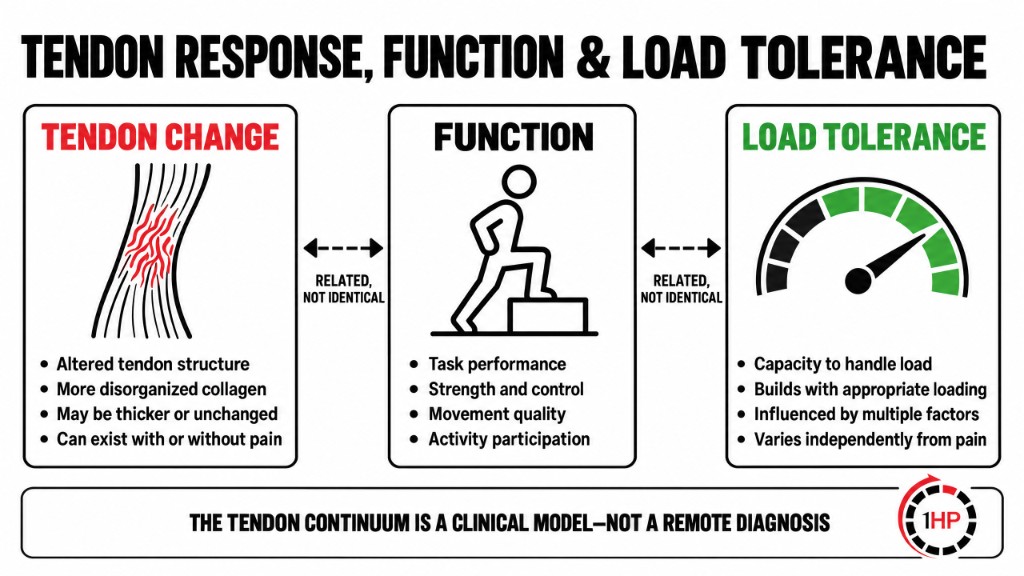
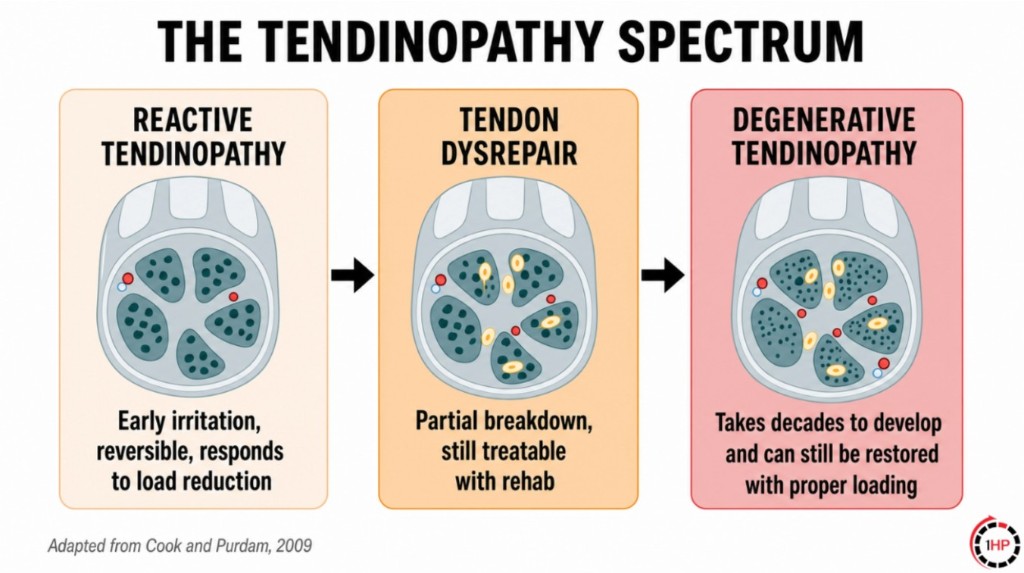
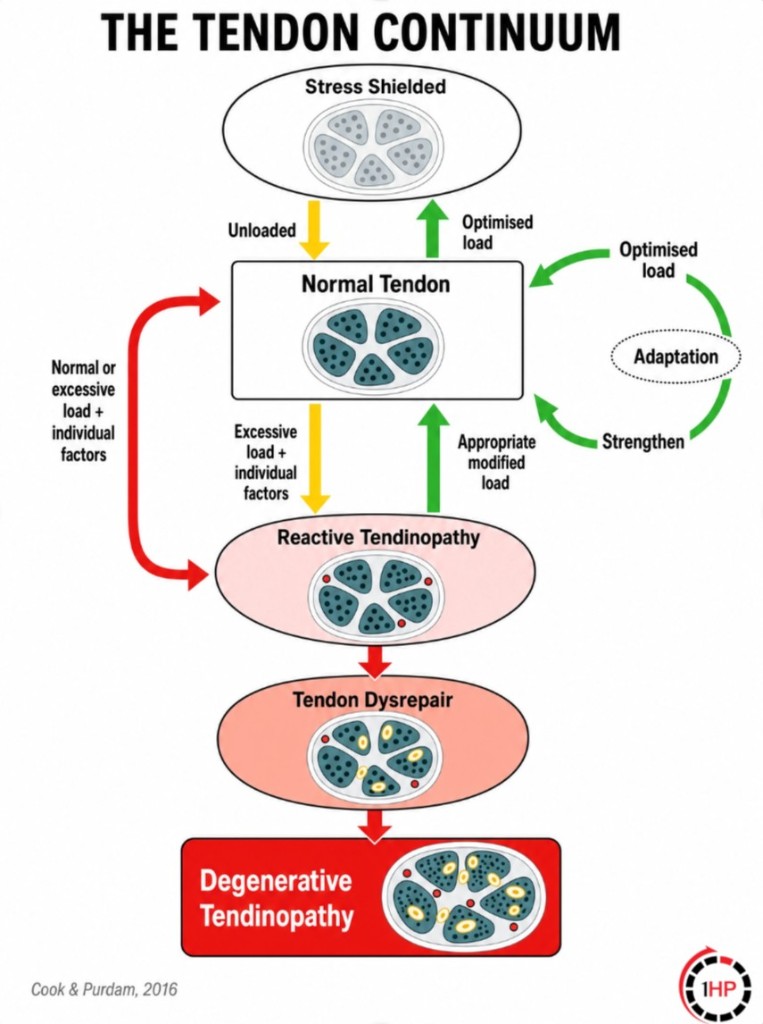
Cook and Purdam's 2009 paper proposed three overlapping tendon states: reactive tendinopathy, tendon dysrepair, and degenerative tendinopathy.[6] In the early reactive state, increased proteoglycans can make a tendon swell after an abrupt load change while much of the collagen remains intact. Later stages include progressively greater matrix disorganisation.
The authors' 2016 update is just as important as the original model: it says that classifying a pain condition from structure alone is incomplete. Pain, function, and structure must be considered together, and their relationship is still not fully understood.[7]
Docking and Cook then used ultrasound tissue characterisation in Achilles and patellar tendons. Pathological tendons contained more disorganised tissue, but because they were thicker, they also contained a greater absolute cross-sectional area of aligned fibrillar structure than normal tendons.[8] That finding supports a capacity-focused question: what can the whole tendon currently tolerate?
What the research actually found
3 stages
Reactive, dysrepair, and degenerative states in the proposed continuum.
91 people
Achilles and patellar tendons examined in the UTC study.
P ≤ .001
More absolute aligned fibrillar structure in pathological tendons.
The 1HP approach
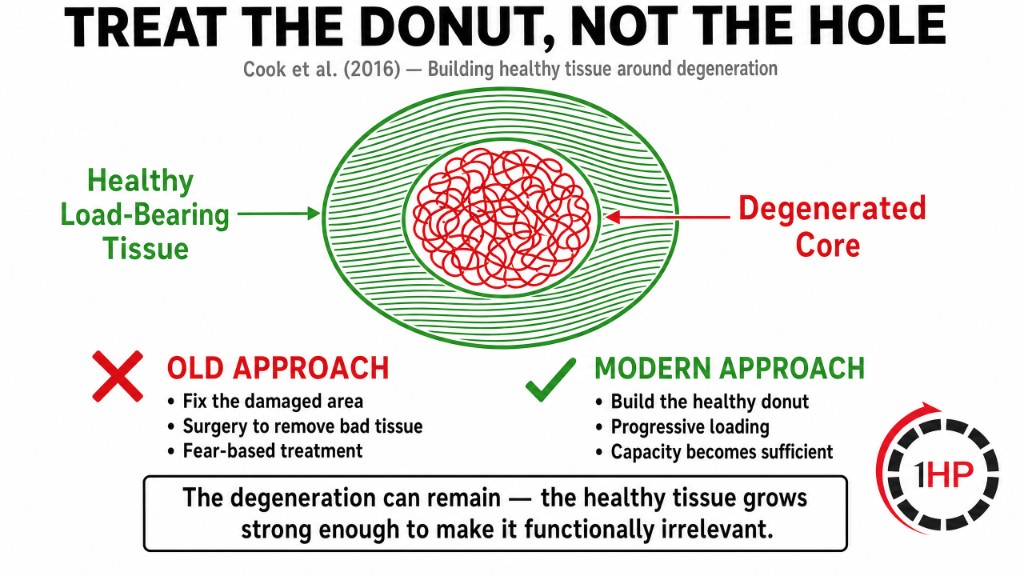
An irritated spot on a scan is often treated as the thing to repair. We assess pain, function, and load tolerance, then build the capacity of the tissue that can still meet the person’s actual demands.
Research limitations and how we bridge the gap
Cook and Purdam built the continuum as a clinical model, and the evidence for healthy, aligned tissue around a damaged area comes from Achilles and patellar tendons, not the forearm. So we measure the forearm directly instead of inferring it from a scan. Each muscle group involved in the symptoms is tested on its own, the same way every time, and the test stops if pain starts to climb, because it measures endurance, not pain tolerance. Loading starts from what that test shows.
One client arrived with seven years of forearm pain and an MRI report of “focal undersurface fraying” where the extensor tendons attach at the outside of the elbow. We loaded that arm anyway: twice a day at a controlled cadence, starting at 5 lb, building to 3 sets of 20, and progressing to 7 lb. By week 20 he was handling work, the gym, and daily life with minimal symptoms. The frayed spot on the report did not set his ceiling. The capacity of the tissue around it did, and that could be trained.
Exercise physiology
Training study + position stand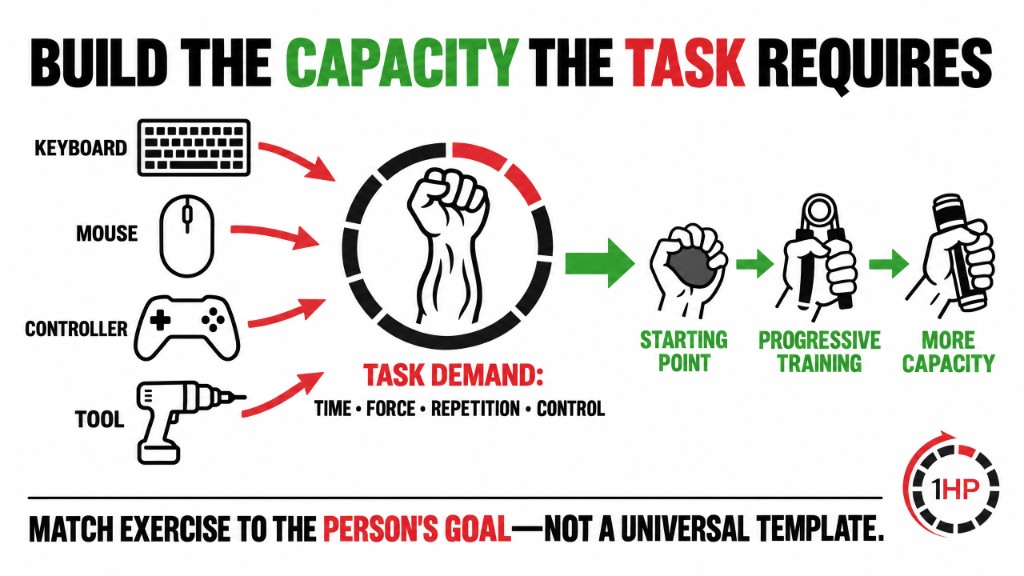
The 1HP approach
Sets copied from another joint are a weak match for repetitive hand use. We use lighter loads and higher repetitions when the goal is local muscular endurance, while still progressing enough resistance to challenge the target tissue. The dose changes with the goal, irritability, and stage of recovery.
Research limitations and how we bridge the gap
Campos and the ACSM position stand mostly describe large-muscle training in healthy adults. Neither gives a forearm dose for a full day at the keyboard and mouse, so we set that target with our own data. Endurance tests from more than 3,000 of our patients show that people who can do 40 to 60 easy repetitions of wrist flexion and extension at 5% of body weight can handle up to 9 to 11 hours of hand use a day, typically 6 to 8 hours of work plus 3 to 4 hours of a hobby.
The program climbs toward that target in earned steps. Reps build first, while the work stays comfortable. Weight goes up only once the current load has been consistently easy, and the reps come back down so the heavier weight starts out tolerable. Amy's recovery followed that shape: 30 reps at 4 lb at the start, 58 to 60 by week 5, then 6 lb with reps reset, and back to 58 to 60 by week 10, across 113 sessions of wrist extension and 114 of wrist flexion. Read Amy's case study
Campos and colleagues compared low-, intermediate-, and high-repetition resistance training for eight weeks. The low-repetition group improved one-repetition maximum the most; the 20–28 repetition-maximum group improved repetitions performed at 60% 1RM the most and was the only group to improve maximal aerobic power and time to exhaustion.[9]
What the study did not show is that high repetitions selectively hypertrophied Type I fibers. In fact, significant fiber-area growth occurred in the lower- and intermediate-repetition groups, not the high-repetition group. The strongest conclusion is specificity of adaptation: strength-focused and endurance-focused doses produced different performance changes.
For local muscular endurance, the 2009 American College of Sports Medicine position stand recommends light to moderate loads, about 40–60% of 1RM, for more than 15 repetitions, with rest under 90 seconds. Its stronger recommendation for novices is 10–15 repetitions with relatively light loads. The underlying trials are mostly large-muscle exercises in healthy adults.[10]
Tendons add another layer. A meta-analysis of 27 healthy-adult studies found meaningful adaptation in tendon stiffness and material properties, with loading magnitude playing an important role.[11] Muscular endurance and tendon adaptation are related targets, but they are not identical.
What the research actually found
32 men
Untrained participants in the eight-week Campos study.
20–28 RM
The group with the largest gain in repetitions at 60% 1RM.
27 studies
Healthy Achilles and patellar tendon interventions in the meta-analysis.
The 1HP approach
Sets copied from another joint are a weak match for repetitive hand use. We use lighter loads and higher repetitions when the goal is local muscular endurance, while still progressing enough resistance to challenge the target tissue. The dose changes with the goal, irritability, and stage of recovery.
Research limitations and how we bridge the gap
Campos and the ACSM position stand mostly describe large-muscle training in healthy adults. Neither gives a forearm dose for a full day at the keyboard and mouse, so we set that target with our own data. Endurance tests from more than 3,000 of our patients show that people who can do 40 to 60 easy repetitions of wrist flexion and extension at 5% of body weight can handle up to 9 to 11 hours of hand use a day, typically 6 to 8 hours of work plus 3 to 4 hours of a hobby.
The program climbs toward that target in earned steps. Reps build first, while the work stays comfortable. Weight goes up only once the current load has been consistently easy, and the reps come back down so the heavier weight starts out tolerable. Amy's recovery followed that shape: 30 reps at 4 lb at the start, 58 to 60 by week 5, then 6 lb with reps reset, and back to 58 to 60 by week 10, across 113 sessions of wrist extension and 114 of wrist flexion. Read Amy's case study
Specific practice
Exercise principle + clinical transfer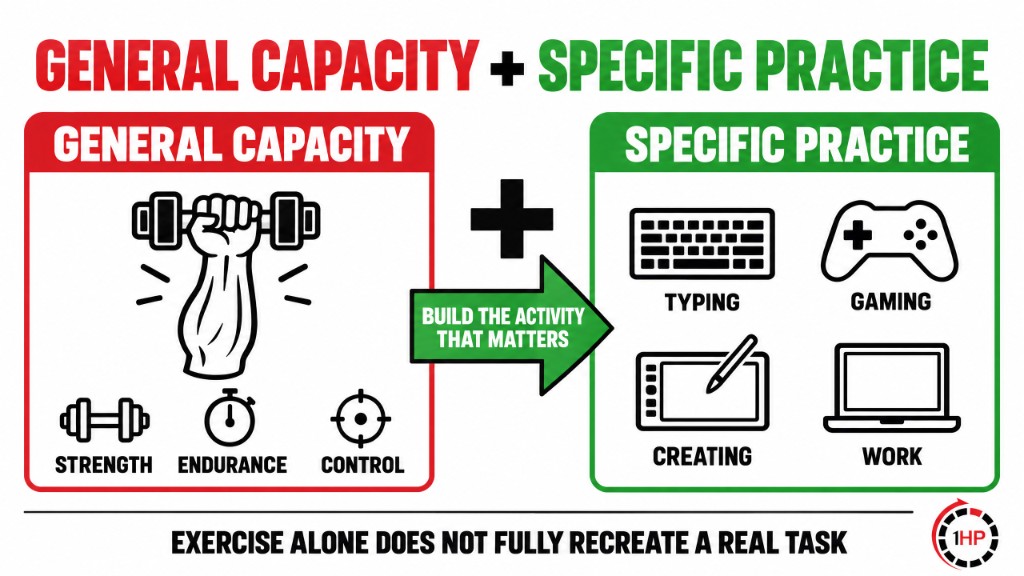
The 1HP approach
A strengthening sheet that never returns to the job, the game, or the instrument leaves the problem unfinished. We pair general wrist, hand, and forearm exercise with measured exposure to the activity that matters. Typing duration, click volume, drawing blocks, practice time, and recovery are progressed like training variables.
Research limitations and how we bridge the gap
No study in this reference set pits exercise alone against exercise plus a graded return to typing, gaming, music, or drawing. Our program does not make people choose. Exercises build general endurance, and the load tracker builds specific endurance in the activity itself, learning how each work or hobby activity affects symptoms and recovery and sizing the next block from that response. People start with the few activities that matter most, usually work and one or two hobbies, so the plan stays simple.
A researcher and programmer was doing about 80% of his technical work by dictation when he started. We progressed the keyboard like a training load, from 80% dictation, to half and half, to 75% on his normal keyboard and mouse, while his exercises moved from 2 to 6 lb. By week 10 he was typing through full workdays and gaming again, including StarCraft 2.
Exercise adaptations are specific to the demand that is trained. In the Campos study, the training zone that best improved maximal strength was not the same zone that best improved repeated-effort performance.[9] The tendon literature also shows that loading conditions influence adaptation.[11]
A wrist curl can improve a useful physical quality, but it does not fully reproduce the duration, speed, coordination, posture, attention, and recovery demands of an eight-hour workday or a long gaming session. Conversely, simply repeating an irritable task may not provide a well-controlled enough stimulus to build general capacity.
That is why our framework uses both. General exercise creates room; structured task practice teaches the person to use that room in the context that matters.
What the research actually found
Strength ≠ endurance
Campos found the largest gains matched the outcome trained.
Load matters
Tendon adaptation varied with the loading conditions used.
No direct trial
The cited studies did not compare wrist curls with typing exposure.
The 1HP approach
A strengthening sheet that never returns to the job, the game, or the instrument leaves the problem unfinished. We pair general wrist, hand, and forearm exercise with measured exposure to the activity that matters. Typing duration, click volume, drawing blocks, practice time, and recovery are progressed like training variables.
Research limitations and how we bridge the gap
No study in this reference set pits exercise alone against exercise plus a graded return to typing, gaming, music, or drawing. Our program does not make people choose. Exercises build general endurance, and the load tracker builds specific endurance in the activity itself, learning how each work or hobby activity affects symptoms and recovery and sizing the next block from that response. People start with the few activities that matter most, usually work and one or two hobbies, so the plan stays simple.
A researcher and programmer was doing about 80% of his technical work by dictation when he started. We progressed the keyboard like a training load, from 80% dictation, to half and half, to 75% on his normal keyboard and mouse, while his exercises moved from 2 to 6 lb. By week 10 he was typing through full workdays and gaming again, including StarCraft 2.
Return to activity
Chronic-pain review + small experiment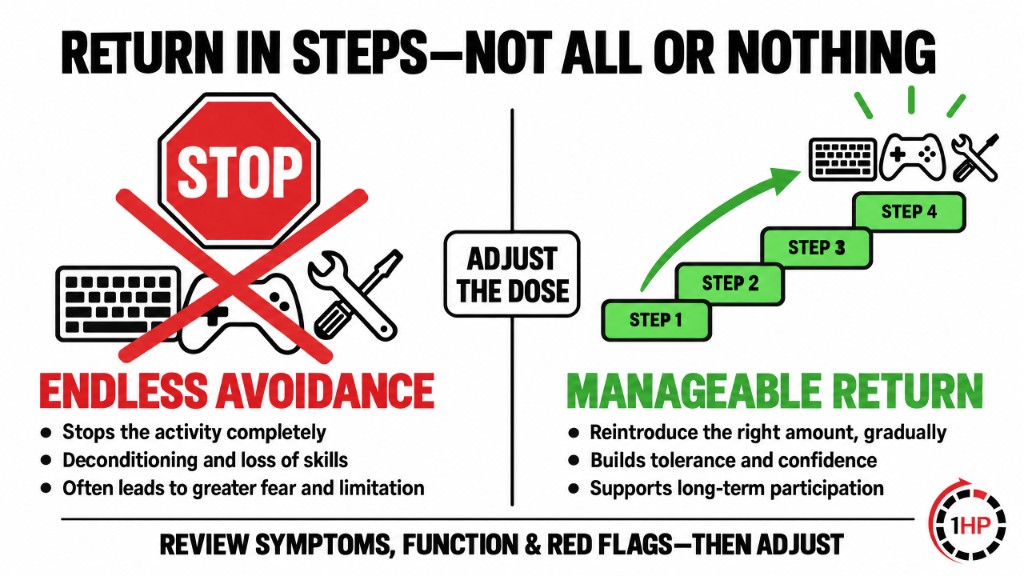
The 1HP approach
Total rest and pushing through are the two plans people are usually given. After appropriate screening, we identify a tolerable dose of the avoided task, repeat it predictably, and progress one variable at a time. A flare leads to review and dose adjustment, and it does not automatically shut the plan down.
Research limitations and how we bridge the gap
Graded exposure was developed and tested in broader chronic pain, including the four-person low-back experiment cited here, so we wrote the principle into rules for hands. The Troubleshooter screens for red flags with 14 questions, and any yes brings a recommendation to see a doctor before continuing. After that, a bad session changes the dose instead of ending the plan. A real spike lowers the load for a short, defined stretch, then steps it back up in stages, and each step waits until symptoms have settled. Training continues through the flare, just lighter, so there is always a clear way back to where the person was.
Julian had tried physical therapy twice. Both times he flared and rested for a week. With us he started at 3 sets of 12 to 15 at 1% of body weight, learned to tell the sharp pain and weakness of tissue strain from the dull ache of working muscles, and took 30 to 40% less load the day after any big push. When a long gaming session spiked his pain in week 8, he treated it as an elevated symptom, not a setback, kept exercising at a lighter load, and it settled within a few days. Read Julian's case study
The fear-avoidance model describes one pathway by which pain can become disabling: threatening interpretations increase fear, fear increases escape and avoidance, and prolonged avoidance can contribute to hypervigilance, guarded movement, disuse, and reduced function.[12]
Graded exposure is different from forcing activity through escalating symptoms. It begins with a specific feared task at a manageable level, tests the person's prediction about harm, and progresses systematically. An early replicated single-case study in four people with chronic low back pain found improvements during the exposure phase rather than the usual graded-activity phase.[13]
The practical principle is “return in steps.” Symptoms, function, recovery time, and red flags are reviewed as the dose changes.
What the research actually found
Fear-avoidance
A model linking threat appraisal, avoidance, disuse, and disability.
4 patients
The early exposure-versus-graded-activity single-case experiment.
Function first
Exposure targets feared activities and predicted harm.
The 1HP approach
Total rest and pushing through are the two plans people are usually given. After appropriate screening, we identify a tolerable dose of the avoided task, repeat it predictably, and progress one variable at a time. A flare leads to review and dose adjustment, and it does not automatically shut the plan down.
Research limitations and how we bridge the gap
Graded exposure was developed and tested in broader chronic pain, including the four-person low-back experiment cited here, so we wrote the principle into rules for hands. The Troubleshooter screens for red flags with 14 questions, and any yes brings a recommendation to see a doctor before continuing. After that, a bad session changes the dose instead of ending the plan. A real spike lowers the load for a short, defined stretch, then steps it back up in stages, and each step waits until symptoms have settled. Training continues through the flare, just lighter, so there is always a clear way back to where the person was.
Julian had tried physical therapy twice. Both times he flared and rested for a week. With us he started at 3 sets of 12 to 15 at 1% of body weight, learned to tell the sharp pain and weakness of tissue strain from the dull ache of working muscles, and took 30 to 40% less load the day after any big push. When a long gaming session spiked his pain in week 8, he treated it as an elevated symptom, not a setback, kept exercising at a lighter load, and it settled within a few days. Read Julian's case study
Motor system
Elbow trial + preliminary studies
The 1HP approach
We use cadence to standardize time under tension, make progression measurable, and support consistent motor practice. It is one programming tool inside a broader loading plan, not the mechanism on which recovery depends.
Research limitations and how we bridge the gap
Rio's immediate pain result comes from six athletes, and the 2025 elbow trial compared paced exercise with stretching and soft-tissue release, not with the same exercise done at a self-chosen pace. So the plan does not rest on the metronome. We use it for reasons that hold either way. A fixed beat lets a retest weeks later compare like with like. It gives rep counts meaning, because a rep only counts the same when it takes the same time, and reps are how progress is read. It also turns every exercise, down to a simple ball squeeze, into controlled, repeatable practice.
We first wrote about tendon neuroplastic training for esports rehab in 2018. The conclusion then is still the one we work from: motor drive is one target, next to tendon load capacity and pain science.
Rio and colleagues compared one bout of isometric and isotonic quadriceps exercise in six athletes with patellar tendinopathy. Isometrics reduced mean pain during a test from 7.0 to 0.17 out of 10, the effect persisted at 45 minutes, and the change occurred alongside reduced cortical inhibition and increased force.[14]
Their 2016 narrative review proposed “tendon neuroplastic training”: heavy strength work paired with external pacing to target both the tendon and motor system.[15] Preliminary participants moved toward more typical inhibition values. We use external pacing so that practice stays consistent while capacity is rebuilt.
A 2025 randomized trial is the first controlled test of this idea in lateral epicondylitis. Thirty-four adults trained three times a week for four weeks. One group did externally paced wrist flexion and extension. The other group received extensor stretching and myofascial release. Paced training reduced pain and tennis-elbow disability more than that comparison, with effect sizes of 0.37 and 0.449. Grip strength improved in both groups, without a clear difference between them.[16]
Paced exercise keeps that loading consistent inside a larger plan. The results clients describe come from the whole method: measure capacity, dose the load, return to the real task, and teach what the pain means. Those stories are on the testimonials page.
What the research actually found
34 adults
Lateral epicondylitis, paced training versus stretching and release for 4 weeks.
0.37
Effect size for greater pain reduction with tendon neuroplastic training.
0.449
Effect size for greater reduction in tennis-elbow disability.
The 1HP approach
We use cadence to standardize time under tension, make progression measurable, and support consistent motor practice. It is one programming tool inside a broader loading plan, not the mechanism on which recovery depends.
Research limitations and how we bridge the gap
Rio's immediate pain result comes from six athletes, and the 2025 elbow trial compared paced exercise with stretching and soft-tissue release, not with the same exercise done at a self-chosen pace. So the plan does not rest on the metronome. We use it for reasons that hold either way. A fixed beat lets a retest weeks later compare like with like. It gives rep counts meaning, because a rep only counts the same when it takes the same time, and reps are how progress is read. It also turns every exercise, down to a simple ball squeeze, into controlled, repeatable practice.
We first wrote about tendon neuroplastic training for esports rehab in 2018. The conclusion then is still the one we work from: motor drive is one target, next to tendon load capacity and pain science.
Daily load management
Clinical theory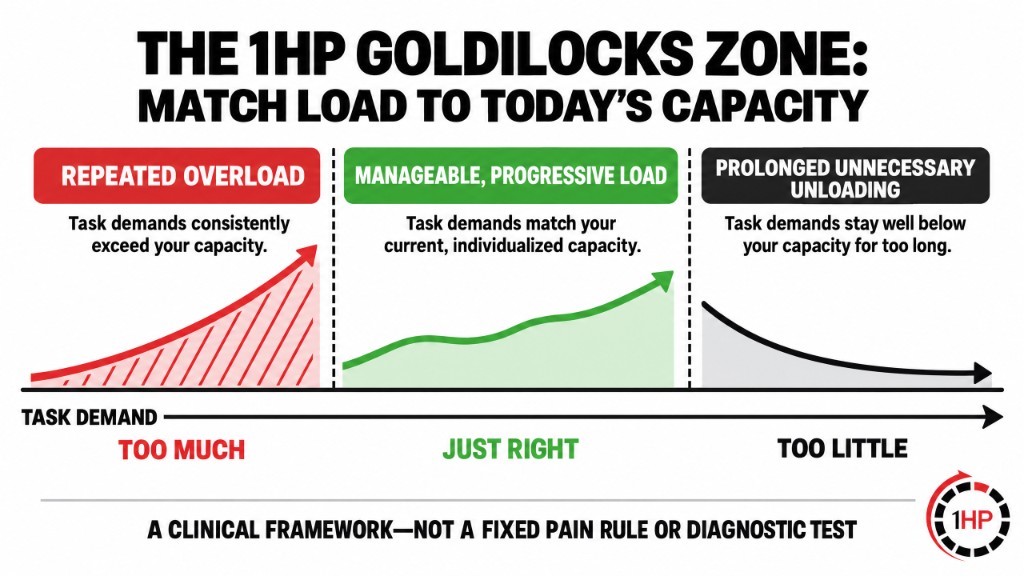
The 1HP approach
A permanent restriction is not the goal. We use symptoms, task performance, recovery, and recent load to estimate today’s workable range, then expand that range through progressive conditioning.
Research limitations and how we bridge the gap
Dye wrote about the knee, and his envelope gives no formula for how long a wrist can work. Our load tracker turns the idea into a daily estimate. It weighs how irritable symptoms are right now, at rest and during the hardest activity, and sizes work and hobby blocks to fit inside today's range. The more irritable the day, the shorter the blocks, and hobbies give way before work does. Calm days that go well earn slightly longer blocks.
That is how a narrow envelope widens on purpose. An animator who was still severely limited after carpal tunnel release surgery began with drawing capped at one hour, split into 30-minute blocks. By week 12 he drew and animated 8 to 10 hours a day for three straight days on a commercial, with some soreness only near the end of the third.
Scott Dye described a joint's “envelope of function” as the range of load and loading frequency it can accept in a period without supraphysiologic overload or structural failure.[17] Anatomy, movement, physiology, and treatment all influence that range.
This gives load management two failure modes. Repeatedly exceeding current capacity can provoke symptoms or injury; prolonged unnecessary underloading can reduce conditioning and narrow what the system can tolerate.
The middle is not a fixed number and it is not synonymous with “zero pain.” It is a continuously reassessed working range in which function is maintained while capacity is built.
What the research actually found
Load × frequency
The original model’s two dimensions of tissue demand.
Knee origin
The theory was developed for a joint under sport and daily loads.
Dynamic range
Anatomy, physiology, movement, and treatment can shift the envelope.
The 1HP approach
A permanent restriction is not the goal. We use symptoms, task performance, recovery, and recent load to estimate today’s workable range, then expand that range through progressive conditioning.
Research limitations and how we bridge the gap
Dye wrote about the knee, and his envelope gives no formula for how long a wrist can work. Our load tracker turns the idea into a daily estimate. It weighs how irritable symptoms are right now, at rest and during the hardest activity, and sizes work and hobby blocks to fit inside today's range. The more irritable the day, the shorter the blocks, and hobbies give way before work does. Calm days that go well earn slightly longer blocks.
That is how a narrow envelope widens on purpose. An animator who was still severely limited after carpal tunnel release surgery began with drawing capped at one hour, split into 30-minute blocks. By week 12 he drew and animated 8 to 10 hours a day for three straight days on a commercial, with some soreness only near the end of the third.
Pain neuroscience
Mechanism review + meta-analysis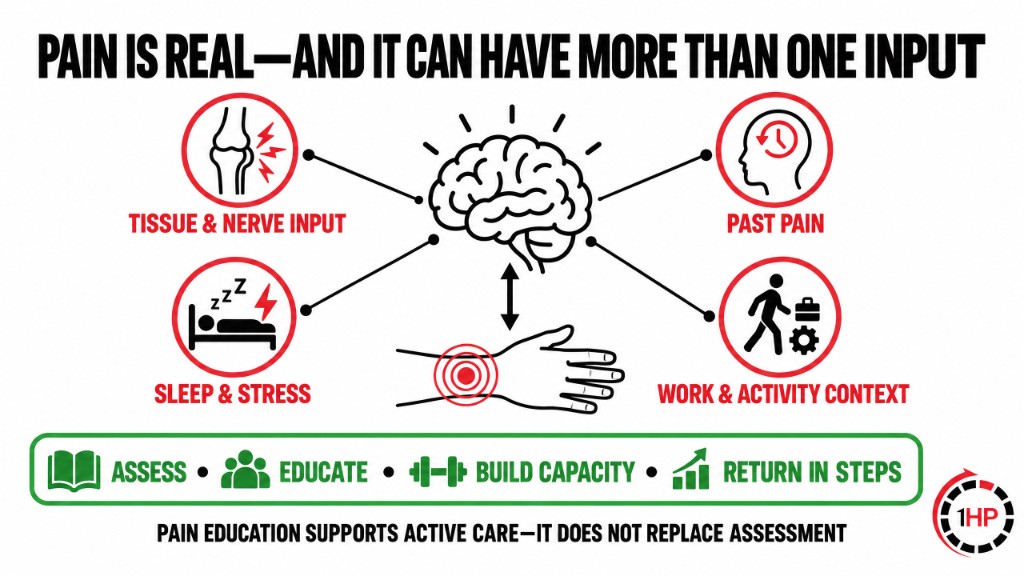
The 1HP approach
Explaining pain and then sending someone home leaves the physical problem untouched. We teach pain science alongside load management, exercise, and task exposure, so the person can make better decisions while capacity is being rebuilt.
Research limitations and how we bridge the gap
Pain-education research mixes many diagnoses, much of it chronic low back pain, and the clearest benefit came when education was paired with physical treatment. That is how we teach it: every lesson ends in something to do. Clients track what they did, not only what hurt, because stopping every time pain shows up can end up rewarding the pain. When symptoms rise, they name the likely cause, whether exercise, activity, sleep and schedule, or stress and fear, change that one factor, and watch the next few days.
Gareth B., a court reporter and gamer, shows why the pairing matters. The Sarno approach had worked for him, then stopped. We treated the underlying tissue problem while teaching him why the psychosomatic approach had helped before, and he resolved six years of wrist pain in 12 weeks. He tells the story on our testimonials page.
Central sensitization describes increased responsiveness in central pain-processing neurons, including amplification and reduced inhibitory control. These are measurable neuroplastic processes, not evidence that pain is imagined.[18]
Louw and colleagues reviewed eight studies with 401 participants and concluded that pain neuroscience education may improve pain, function, catastrophizing, and movement in chronic musculoskeletal pain.[19] The studies were too heterogeneous for a meta-analysis, and most involved chronic low back pain.
A 2025 systematic review and meta-analysis included 19 randomized trials and 693 adults receiving pain neuroscience education with a physical therapy intervention. Across the intervention groups, mean pain scores decreased from 5.89 to 3.03, which is nearly half and can be stated conservatively as roughly a 45% reduction. Disability outcomes also improved across the included measures. The controlled random-effects analysis estimated a 0.784-point advantage on a 0–10 pain scale in favor of combined care, with moderate certainty but high heterogeneity.[20]
Moseley and Butler's later review likewise frames education as part of a broader clinical approach.[21] Information can change the meaning of pain, but meaningful recovery still requires active practice and restored function.
What the research actually found
19 RCTs
Included in the 2025 systematic review and meta-analysis.
≈45% lower
Mean pain scores fell from 5.89 to 3.03 across intervention groups.
0.78 points
Pooled comparative benefit on a 0–10 pain scale.
The 1HP approach
Explaining pain and then sending someone home leaves the physical problem untouched. We teach pain science alongside load management, exercise, and task exposure, so the person can make better decisions while capacity is being rebuilt.
Research limitations and how we bridge the gap
Pain-education research mixes many diagnoses, much of it chronic low back pain, and the clearest benefit came when education was paired with physical treatment. That is how we teach it: every lesson ends in something to do. Clients track what they did, not only what hurt, because stopping every time pain shows up can end up rewarding the pain. When symptoms rise, they name the likely cause, whether exercise, activity, sleep and schedule, or stress and fear, change that one factor, and watch the next few days.
Gareth B., a court reporter and gamer, shows why the pairing matters. The Sarno approach had worked for him, then stopped. We treated the underlying tissue problem while teaching him why the psychosomatic approach had helped before, and he resolved six years of wrist pain in 12 weeks. He tells the story on our testimonials page.
Diagnosis and imaging
Asymptomatic imaging studies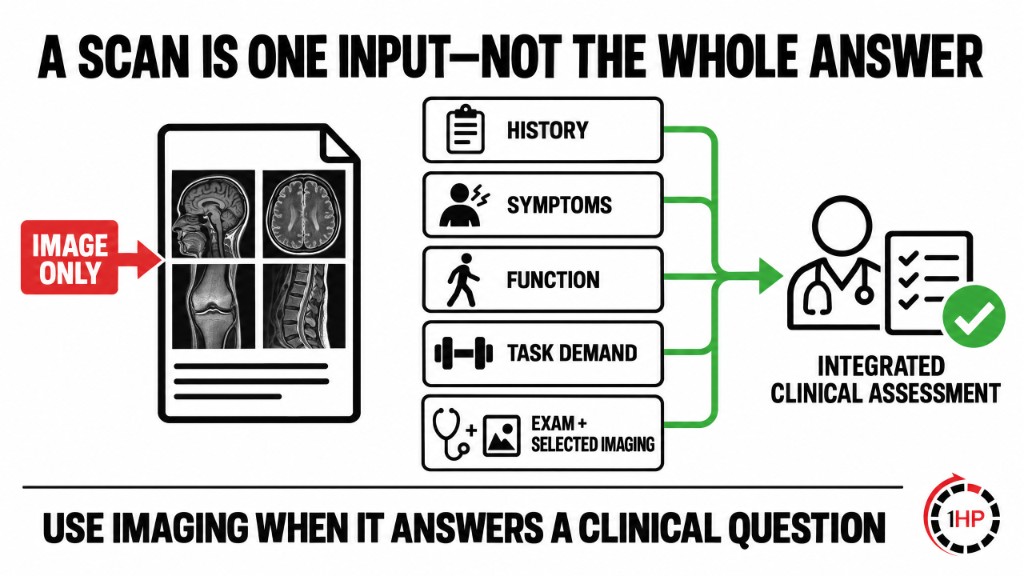
The 1HP approach
An abnormal scan is often handed over as the cause. We read it inside symptom behavior, neurological signs, function, load history, examination, and red flags, then measure capacity because structure alone cannot tell us what a person can do.
Research limitations and how we bridge the gap
Asymptomatic imaging studies show that structural findings are common without pain. They cannot say whether the finding on your report is the one causing yours. We answer that in the exam, by checking whether the finding matches where it hurts, what provokes it, and what the hand can still do.
A student and gamer with pain on the palm side of his wrist asked for an MRI, which showed a minor partial tear of the scapholunate ligament on the back of the wrist. Four findings said it was not the driver: he could bear full weight and bench press heavy without pain, his pain was on the opposite side from the ligament, stressing the ligament in full flexion did not hurt, and light repetitive hand use does not load that joint. The tear was most likely a normal age-related change. He kept training, had normal endurance in that wrist by week 9, and had no pain with any activity by week 16.
Imaging is essential when the clinical question requires it: suspected fracture, significant trauma, mass, surgical planning, or another condition in which structure changes management. The problem is treating every finding as a complete explanation.
In one study, 19 asymptomatic professional baseball pitcher draft picks received high-resolution MRI of the dominant shoulder. Thirteen showed tendinopathy, six showed partial-thickness supraspinatus tears, and four showed acromioclavicular osteoarthritis.[22]
Those shoulder numbers do not transfer directly to the wrist. A wrist MRI study of 103 asymptomatic volunteers does address that joint. Three readers judged the triangular fibrocartilage complex abnormal in 39 wrists, including a complete tear in 23. The abnormal group included 31 volunteers younger than 50, 5 aged 50 to 59, and all 3 volunteers older than 60. Older age was correlated with an abnormal TFCC (rpb = 0.23; P = .016).[23]
The shared boundary is that a structural feature can exist without symptoms. Imaging still answers some clinical questions, but an abnormal scan has to be matched to the history and examination rather than treated as a complete explanation by itself.
What the research actually found
103 wrists
Asymptomatic volunteers imaged with 1.9-T wrist MRI.
39 of 103
Had a TFCC read as abnormal despite no symptoms.
23 of 103
Were read as having a complete TFCC tear.
The 1HP approach
An abnormal scan is often handed over as the cause. We read it inside symptom behavior, neurological signs, function, load history, examination, and red flags, then measure capacity because structure alone cannot tell us what a person can do.
Research limitations and how we bridge the gap
Asymptomatic imaging studies show that structural findings are common without pain. They cannot say whether the finding on your report is the one causing yours. We answer that in the exam, by checking whether the finding matches where it hurts, what provokes it, and what the hand can still do.
A student and gamer with pain on the palm side of his wrist asked for an MRI, which showed a minor partial tear of the scapholunate ligament on the back of the wrist. Four findings said it was not the driver: he could bear full weight and bench press heavy without pain, his pain was on the opposite side from the ligament, stressing the ligament in full flexion did not hurt, and light repetitive hand use does not load that joint. The tear was most likely a normal age-related change. He kept training, had normal endurance in that wrist by week 9, and had no pain with any activity by week 16.
Rest and deconditioning
Review + healthy-volunteer studies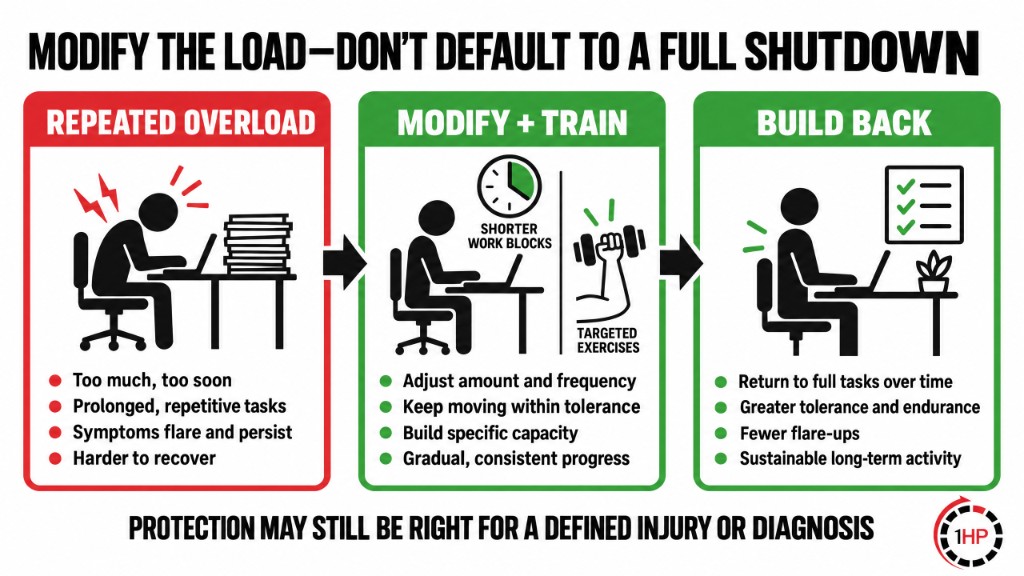
The 1HP approach
Weeks of complete rest are a common first prescription. When protection is medically indicated, we respect it. When complete rest is not required, we keep tolerable movement and plan progressive reloading so the solution does not create a second capacity problem.
Research limitations and how we bridge the gap
Casting and bed rest produce the largest losses in these studies, and both are far more extreme than easing off the keyboard. In our experience the everyday version still adds up: most people who have been in pain for a long time are underloading, not overloading. That does not make rest the enemy. Planned rest days are built into the program, and taking one does not break your streak. What we avoid is open-ended unloading.
Michael had radial tunnel surgery, which fixed the nerve compression but left the tendon problem untouched. Voice control, an eye tracker, and a 20-minute keyboard timer followed, and five minutes of typing still stopped him. Our test showed the mismatch: 55 to 60 reps at 4 lb, stopped by fatigue rather than pain, about 60% of his target, while he had been training with 1 to 2 lb in broken sets. We moved him to 4 lb right away, with continuous reps at 50 beats per minute. He was back to heavy lifting by week 7 and typing full workdays by month 5. Read Michael's case study
A broad review of training and immobilization described reductions in muscle size, capillary density, and tendon or ligament properties with unloading, while noting that much of the tendon evidence available at the time came from animal work.[24] In one experiment from that literature, the rat gastrocnemius muscle-tendon unit was cast for up to three weeks. Force to failure fell by 21% when the muscle was held lengthened and 31% when it was held shortened after one week, and by about 26% and 48% after three weeks. Energy absorbed before failure fell 49% in the lengthened position and 64% in the shortened position. The unit lost 12% of its weight when lengthened and 36% when shortened. Elastic stiffness fell in both positions, but that report did not give a separate percentage for the stiffness loss.[25]
In eight healthy men, 20 days of bed rest reduced knee-extensor tendon stiffness from 70.3 to 50.1 N/mm, about 29% lower, and increased hysteresis. The plantar-flexor stiffness change did not meet statistical significance.[26] This was a lower-limb model, not a wrist study.
More directly relevant to the upper limb, Motobe and colleagues placed 14 healthy men in forearm casts for 21 days. Muscle oxidative recovery worsened in the immobilization group, and endurance training twice weekly prevented some of the decline; grip strength still fell in both groups.[27]
What the research actually found
20 days
Bed rest in eight healthy men in the Kubo tendon study.
70.3 → 50.1
N/mm knee-extensor tendon stiffness before versus after.
21 days
Forearm casting in 14 healthy men in the Motobe study.
The 1HP approach
Weeks of complete rest are a common first prescription. When protection is medically indicated, we respect it. When complete rest is not required, we keep tolerable movement and plan progressive reloading so the solution does not create a second capacity problem.
Research limitations and how we bridge the gap
Casting and bed rest produce the largest losses in these studies, and both are far more extreme than easing off the keyboard. In our experience the everyday version still adds up: most people who have been in pain for a long time are underloading, not overloading. That does not make rest the enemy. Planned rest days are built into the program, and taking one does not break your streak. What we avoid is open-ended unloading.
Michael had radial tunnel surgery, which fixed the nerve compression but left the tendon problem untouched. Voice control, an eye tracker, and a 20-minute keyboard timer followed, and five minutes of typing still stopped him. Our test showed the mismatch: 55 to 60 reps at 4 lb, stopped by fatigue rather than pain, about 60% of his target, while he had been training with 1 to 2 lb in broken sets. We moved him to 4 lb right away, with continuous reps at 50 beats per minute. He was back to heavy lifting by week 7 and typing full workdays by month 5. Read Michael's case study
From papers to practice
No single paper proves the entire system. We connect compatible findings with what clinical work has shown us, measure the individual response, and change course when that response does not match the plan. The client stories are on the testimonials page.
01
Screen for red flags, understand the symptom pattern, and measure current functional capacity.
02
Build strength and endurance with a dose chosen for the target and today’s irritability.
03
Progress the real activity so physical gains become usable work, play, music, or creative capacity.
04
Track function, recovery, confidence, and symptoms; then adjust instead of following a rigid protocol.
The free 1HP wrist pain guide helps you identify the relevant region, understand the tissues involved, and take the first structured step.
If your case needs individual application
A free consultation is where we discuss your symptom pattern, current endurance, daily demands, previous treatment, and whether 1HP's approach is appropriate. It is not a substitute for urgent or in-person medical care when that is needed.
Source library
Links open the paper, abstract, or full-text record. Reference numbers match the citations throughout this page.
McGee C, Hwu M, Nicholson LL, Ho KKN. More than a game: musculoskeletal injuries and a key role for the physical therapist in esports. Journal of Orthopaedic & Sports Physical Therapy. 2021;51(9):415-417.
Hwu M, McGee C, Rodriguez AG, et al. Corrective exercise and physical training guidelines for esport athletes and teams. Conditioning for Esports: A Guide to Training and Performance. Human Kinetics. 2025. Chapters 8-10.
Smithson EV, Reed Smith E, McIlvain G, Timmons MK. Effect of arm position on width of the subacromial space of upper string musicians. Medical Problems of Performing Artists. 2017;32(3):159-164.
McGee C, Ho K. Tendinopathies in video gaming and esports. Frontiers in Sports and Active Living. 2021;3:689371.
Schary DP, Jenny SE, Koshy A. Leveling up esports health: current status and call to action. International Journal of Esports. 2022;1(1).
Cook JL, Purdam CR. Is tendon pathology a continuum? A pathology model to explain the clinical presentation of load-induced tendinopathy. British Journal of Sports Medicine. 2009;43(6):409-416.
Cook JL, Rio E, Purdam CR, Docking SI. Revisiting the continuum model of tendon pathology: what is its merit in clinical practice and research? British Journal of Sports Medicine. 2016;50(19):1187-1191.
Docking SI, Cook J. Pathological tendons maintain sufficient aligned fibrillar structure on ultrasound tissue characterisation (UTC). Scandinavian Journal of Medicine & Science in Sports. 2016;26(6):675-683.
Campos GE, Luecke TJ, Wendeln HK, et al. Muscular adaptations in response to three different resistance-training regimens: specificity of repetition maximum training zones. European Journal of Applied Physiology. 2002;88(1-2):50-60.
Ratamess NA, Alvar BA, Evetoch TK, et al. American College of Sports Medicine position stand. Progression models in resistance training for healthy adults. Medicine & Science in Sports & Exercise. 2009;41(3):687-708.
Bohm S, Mersmann F, Arampatzis A. Human tendon adaptation in response to mechanical loading: a systematic review and meta-analysis of exercise intervention studies on healthy adults. Sports Medicine - Open. 2015;1(1):7.
Vlaeyen JWS, Linton SJ. Fear-avoidance and its consequences in chronic musculoskeletal pain: a state of the art. Pain. 2000;85(3):317-332.
Vlaeyen JWS, de Jong J, Geilen M, Heuts PHTG, van Breukelen G. Graded exposure in vivo in the treatment of pain-related fear: a replicated single-case experimental design in four patients with chronic low back pain. Behaviour Research and Therapy. 2001;39(2):151-166.
Rio E, Kidgell D, Purdam C, et al. Isometric exercise induces analgesia and reduces inhibition in patellar tendinopathy. British Journal of Sports Medicine. 2015;49(19):1277-1283.
Rio E, Kidgell D, Moseley GL, et al. Tendon neuroplastic training: changing the way we think about tendon rehabilitation: a narrative review. British Journal of Sports Medicine. 2016;50(4):209-215.
Khan H, Razzaq A, Afridi A, Sheraz S, Awan WA. Innovative neuroplastic healing: tendon neuroplastic training role in pain alleviation and boosting strength in lateral epicondylitis: a randomized controlled trial. BMC Musculoskeletal Disorders. 2025;26:949.
Dye SF. The knee as a biologic transmission with an envelope of function: a theory. Clinical Orthopaedics and Related Research. 1996;(325):10-18.
Latremoliere A, Woolf CJ. Central sensitization: a generator of pain hypersensitivity by central neural plasticity. The Journal of Pain. 2009;10(9):895-926.
Louw A, Diener I, Butler DS, Puentedura EJ. The effect of neuroscience education on pain, disability, anxiety, and stress in chronic musculoskeletal pain. Archives of Physical Medicine and Rehabilitation. 2011;92(12):2041-2056.
Sánchez-Robalino A, Sinchi-Sinchi H, Ramírez A. Effectiveness of Pain Neuroscience Education in Physical Therapy: A Systematic Review and Meta-Analysis. Brain Sciences. 2025;15(6):658.
Moseley GL, Butler DS. Fifteen years of explaining pain: the past, present, and future. The Journal of Pain. 2015;16(9):807-813.
Del Grande F, Aro M, Farahani SJ, et al. High-resolution 3-T magnetic resonance imaging of the shoulder in nonsymptomatic professional baseball pitcher draft picks. Journal of Computer Assisted Tomography. 2016;40(1):118-125.
Iordache SD, Rowan R, Garvin GJ, Osman S, Grewal R, Faber KJ. Prevalence of triangular fibrocartilage complex abnormalities on MRI scans of asymptomatic wrists. Journal of Hand Surgery. 2012;37(1):98-103.
Kannus P, Jozsa L, Renstrom P, et al. The effects of training, immobilization and remobilization on musculoskeletal tissue. Part 1: Training and immobilization. Scandinavian Journal of Medicine & Science in Sports. 1992;2(3):100-118.
Järvinen M, Einola S, Virtanen E. Effect of the position of immobilization upon the tensile properties of the rat gastrocnemius muscle. Archives of Physical Medicine and Rehabilitation. 1992;73(3):253-257.
Kubo K, Akima H, Ushiyama J, et al. Effects of 20 days of bed rest on the viscoelastic properties of tendon structures in lower limb muscles. British Journal of Sports Medicine. 2004;38(3):324-330.
Motobe M, Murase N, Osada T, et al. Noninvasive monitoring of deterioration in skeletal muscle function with forearm cast immobilization and the prevention of deterioration. Dynamic Medicine. 2004;3:2.
Medical disclaimer: This page provides general education and does not diagnose a condition, prescribe an individual treatment plan, or replace care from a qualified healthcare professional. Seek prompt medical evaluation for significant trauma, rapidly worsening weakness or sensation loss, major swelling or discoloration, fever, or other urgent symptoms.